
Revision joint replacement
Revision Knee Replacement
Revision knee replacement is the operation in which a previous artificial joint that has failed for some reason is replaced with a new one. It is a technically demanding, major operation that requires considerable experience and specialisation on the part of the Orthopedic Surgeon.
Dr. Ioannis Tsarouhas, Orthopedic Surgeon with particular specialisation in revisions of major joint replacements, handles these complex operations with great experience, with the aim of restoring the patient’s stability, function and quality of life.
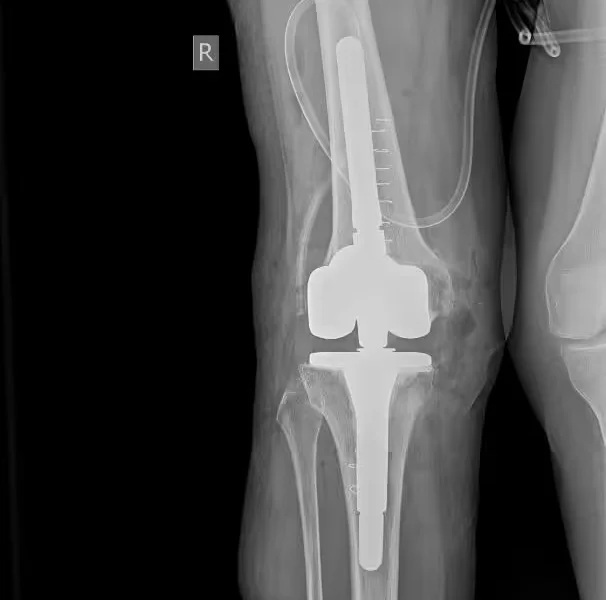
What is revision knee replacement?
Total knee replacement is one of the most successful operations in modern orthopedics, with excellent longevity. However, no artificial joint necessarily lasts for ever. Over the years —or, more rarely, because of a complication— a knee replacement may fail and need to be replaced.
Revision is precisely this operation: the removal of the old, problematic implants and the placement of new ones, specially designed for revision. As the number of patients with a joint replacement increases —and indeed at younger ages— revision operations are becoming more and more common.
When is revision needed?
The main reasons why a knee replacement may need revision are:
- Loosening of the implants: The progressive loss of the secure fixation of the prosthesis to the bone, most often because of polyethylene wear (aseptic loosening).
- Infection: One of the most serious causes of failure, which requires particular, specialised treatment.
- Polyethylene wear: The gradual wear of the plastic insert that acts as the “cartilage”.
- Instability: When the joint is not sufficiently stable, because of soft-tissue imbalance or other factors.
- Stiffness: Severe restriction of the range of motion that does not respond to other treatments.
- Periprosthetic fracture: A fracture of the bone around the prosthesis.
Accurate identification of the cause of failure is the first and most critical step, as it determines the revision strategy.
Diagnosis and pre-operative work-up
Before any decision to revise, a detailed investigation of the cause of failure is required. The work-up includes:
- Clinical examination and history, with emphasis on the character of the pain and how it has evolved over time.
- Radiographs, which show loosening, migration, wear or fracture, and can also be used to assess bone stock and plan the operation.
- Laboratory tests for inflammatory markers, to exclude or confirm infection.
- Aspiration of the joint with culture, when a septic cause is suspected.
The distinction between aseptic and septic failure is particularly critical, as the treatment differs radically.
How revision is performed
The revision operation is technically much more demanding than the original knee replacement. Unlike the primary operation, the surgeon works in an already altered anatomy, with scar tissue and, often, bone defects.
In general, revision involves the careful removal of the old implants —preserving as much healthy bone as possible— meticulous debridement of the area, reconstruction of the bone defects (with bone grafts or special metal augments), and the implantation of special revision prostheses, which are often anchored more deeply and more securely in the bone and provide a greater degree of stability. At the end, stability, ligament balance and range of motion are checked.
The special case of infection
When the cause of failure is infection, treatment is as a rule carried out in two stages: first the implants are removed and a temporary antibiotic-loaded spacer is inserted, followed by a period of intensive antibiotic therapy to eradicate the infection, and at a second stage —once it has been confirmed that the infection has resolved— the definitive prosthesis is implanted. Management is carried out in collaboration with an Infectious Diseases specialist.
The difference from primary knee replacement
Many patients wonder why revision is considered so much more demanding than the original knee replacement, when “it is the same knee”. The answer lies in the conditions under which the surgeon works.
In primary knee replacement, the surgeon works on “virgin” anatomical ground, with normal anatomy and healthy bone. In revision, by contrast, they must first remove the existing implants —often well fixed— without destroying healthy bone, deal with the scar tissue from the previous operation, and address the bone defects that have already formed. In addition, they must restore stability in an environment where the normal stabilisers (ligaments, bone) may have been weakened. It is this complexity that makes the surgeon’s experience and specialisation so decisive.
Post-operative course and rehabilitation
Rehabilitation after revision knee replacement is as a rule longer and more cautious than after the primary operation. Its pace depends on the extent of the intervention, the quality of the bone and any need to protect bone grafts.
Mobilisation begins with walking aids and protected weight-bearing, in accordance with the surgeon’s instructions. The physiotherapy programme focuses on restoring range of motion, strengthening the muscles and gait retraining, at a pace adapted to each case. Patience and consistency are particularly important here.
What results should I expect?
Revision knee replacement offers the great majority of patients significant pain relief, restoration of stability and a substantial improvement in function. It is, however, important that expectations are realistic: the functional result of a revision, although as a rule very good, may not fully match that of an excellently functioning primary knee replacement, especially in cases with large bone defects or previous infection.
The surgeon’s specialisation and experience are decisive here. Revision operations are as a rule performed by surgeons with specific experience in them, as the quality of treatment directly affects the outcome.
Why revisions are increasing
The number of revision operations is rising internationally, and this does not mean that joint replacements are failing more often — on the contrary, modern implants are more durable than ever. The real reason is twofold.
On the one hand, far more primary joint replacements are now performed than in the past, so the absolute number of those that will, over time, need revision also rises. On the other hand, joint replacements are now also performed in younger, more active patients, who place demands on the prosthesis for more years. The good news is that, alongside demand, treatment options have also advanced spectacularly, so that revision can today offer excellent results, even in complex cases.
The role of the specialised centre and surgeon
Revision knee replacement ranks among the most demanding operations in orthopedics. Unlike primary knee replacement, the surgeon has to manage an already altered anatomy, bone defects, scar tissue and, sometimes, infection. Each of these elements increases the technical difficulty and requires experience, special equipment and access to the full range of specialised revision implants.
It is precisely for this reason that revision operations are as a rule performed by surgeons with specific experience in them. Choosing the right surgeon is not merely a preference but a decisive factor for the outcome: a correctly planned and executed revision can substantially restore the patient’s function and quality of life.
Cost of revision knee replacement
The cost of revision varies more widely than that of the primary operation, as it depends on the cause and extent of the intervention, the specialised implants and materials that will be required, the possible need for two-stage treatment in the event of infection, the hospital and the length of stay, as well as the patient’s insurance cover. In most cases, private insurance policies and insurance funds cover a significant part of the expense.
Precise information is provided on an individual basis, after completion of the diagnostic work-up. The practice is at your disposal for any relevant information.
More on the factors that determine the cost and on cover by insurance funds: Cost of surgery.
Realistic expectations and information
An important part of preparing for a revision is informing the patient properly and forming realistic expectations. Revision offers, in the great majority of cases, substantial pain relief and a significant improvement in function.
It is, however, a more complex operation than the original one, with a longer rehabilitation and a functional result which, although as a rule very good, depends on factors such as the cause of failure, the quality of the remaining bone and the condition of the soft tissues. Honest information about all of this, combined with the surgeon’s experience, is what ensures the patient’s satisfaction with the final result.
Frequently asked questions
Why might a knee replacement need revision?
The most common causes are loosening of the implants, infection, polyethylene wear, instability, stiffness and periprosthetic fractures. The exact cause determines the revision strategy.
Is it more difficult than the original knee replacement?
Yes. Revision is technically more demanding, as it involves removing the old implants, managing bone defects and using specialised prostheses. It must be performed by a surgeon with specific experience.
What happens if there is infection?
In the event of infection, treatment is as a rule carried out in two stages: removal of the implants and insertion of a temporary antibiotic spacer, and at a second stage —once the infection has been eradicated— implantation of the definitive prosthesis.
How long does recovery take?
Rehabilitation is as a rule longer than after primary knee replacement and depends on the extent of the intervention, the quality of the bone and compliance with the physiotherapy programme.
Will the knee function normally after revision?
The aim is to restore pain-free, stable function. The great majority of patients achieve significant improvement, although the result may not fully match that of an excellent primary knee replacement.
Is the cost covered by insurance?
In most cases, private insurance policies and insurance funds cover part or all of the expense. The practice can give you detailed information.
How many times can a knee replacement be revised?
There is no absolute limit; as many revisions as are required can be performed, depending on the problem. The limit is usually set by excessive loss of bone mass, persistent infection or the patient’s general state of health.
Do all the implants always need to be replaced?
Not necessarily. Depending on the cause, revision may in some cases be limited to a partial intervention, provided parts of the prosthesis are stable and correctly positioned. The extent is determined after the diagnostic work-up.
How often does a knee replacement need revision?
Modern knee replacements have excellent longevity and many last 15-20 years or even longer. A proportion, however, will at some point need revision, especially in younger and active patients who place demands on the prosthesis for more years.
Is revision safe?
Yes, when it is performed by an experienced surgeon in an appropriate setting. It is a major operation with its own risks, which are, however, minimised with correct planning, specialisation and careful rehabilitation.
Contact
Book an appointment with Dr. Tsarouhas
Fill in the form with the time that suits you and we will contact you, or call us directly.
Call us 210 6464 744-
Petroupoli 1 Agias Triados St., 132 31 210 5011 717
-
Heraklion, Crete 49 Kyrillou Loukareos St., 712 01
Appointment request
We reply to every request on the same or the next working day.
Your details are used solely to contact you.